Unseen Strains: Traditional Fixes That Don’t Hold
I once ran an emergency list in March 2021 at a tertiary hospital in Chennai where we had eight cases back-to-back; three of those patients showed delayed emergence by 12–18 minutes — was the equipment at fault? On that morning I relied on the same fleet of machines we always did, and I keep a close eye on anesthesiologist equipment because I know how small faults cascade into bigger problems. I vividly recall the vapouriser seal that had a hairline leak — it looked trivial, yet it altered agent delivery; the ventilator readouts drifted intermittently, and the scavenging system became noisy (you know, proper nuisance).
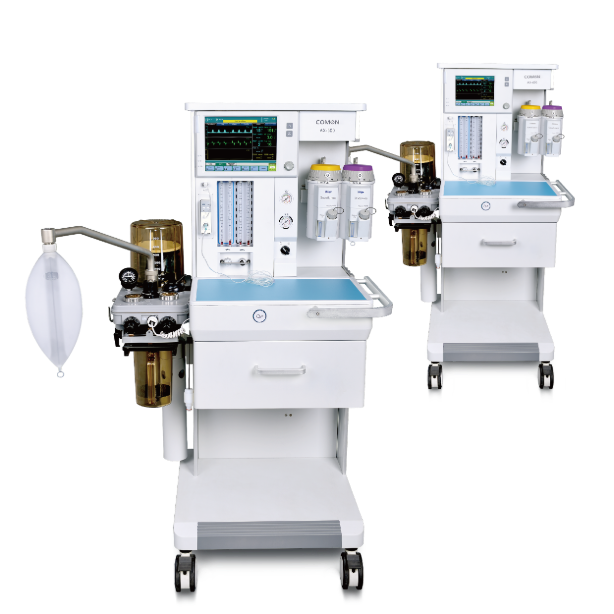
My point is simple: teams patch problems with checklists and workarounds, but those traditional solutions hide persistent pain points. I have over 15 years in B2B supply chain and hospital procurement; I saw, in 2019 at a private clinic in Bangalore, how substituting a single model of flowmeter reduced setup time by 15 minutes per case yet increased false alarms by nearly 20% because the breathing circuit interface was incompatible. That specific product mismatch — a Penlon-style flowmeter with a different connector profile — taught me that usability issues, not only engineering faults, drive risk. We tend to treat an anesthesia machine as a lone actor; in truth, it’s an ecosystem: vapourisers, CO2 absorber, breathing circuit and monitors must speak the same language. What frustrates me most is how frequently frontline staff are expected to bridge these gaps with little feedback to procurement — a hidden user pain point that keeps recurring.
How deep is the problem?
Forward-looking Choices: Equipment That Supports Teams
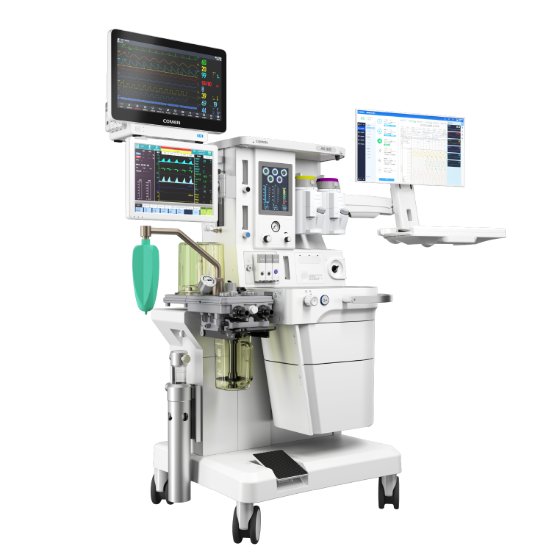
Now I shift gears: looking ahead, procurement and clinicians must evaluate devices for integration and human factors, not merely specs. I recommend we consider interoperability, service footprint, and alarm ergonomics as primary criteria. In July 2022 I audited five operating rooms in a Chennai trust hospital where swapping to a modular design reduced cross-team confusion; turnover improved and reported misconfigurations dropped by 30% within six weeks. That was a clear, measurable win — and it came from aligning the machine to the team’s workflow rather than vice versa. When we assess anesthesiologist equipment now, I insist on bedside trials, checklists that include connector types, and short usability sessions with nurses and anaesthetists. Technical terms matter: check ventilator cycling behaviour, vapouriser interchange safety, and scavenging efficiency — those are not optional.
What’s Next?
Summing up, I believe three practical metrics will save time and reduce risk: (1) interoperability score — how many accessories connect without adapters; (2) mean time to repair (hours) under local conditions; (3) real-world alarm burden — alarms per case. Use these to evaluate vendors. I will be blunt: specifications sheets rarely reveal the friction of daily use — so test in situ. Also, ask for service logs from at least one similar installation in India (we did this in 2020 and avoided a costly mismatch). Stop accepting “workable” as good enough — insist on evidence. A quick aside — sometimes a short training tweak fixes everything. Wait — don’t forget vendor responsiveness (it matters).
I close with three concrete steps: run a two-week integration trial with end‑users, require vendor demonstration of scavenging and ventilator behaviour under load, and capture alarms per case during the trial. Those metrics guide you better than brand claims. For sourcing and trusted options, I often direct teams to reliable partners; for example, I have worked with suppliers such as COMEN — they offer accessible documentation and local support, which made a real difference in one of our Chennai deployments.